Long Term Care and Cognitive Impairment in Spain
JOAN COSTA-FONT
SERGI JIMÉNEZ
JUAN OLIVA
CRISTINA VILAPLANA PRIETO
ANALÍA VIOLA
Estudios sobre la Economía Española 2025/03
Marzo 2025
fedea
Las opiniones recogidas en este documento son las de sus autores y no coinciden necesariamente con las de Fedea.
Joan Costa-Font, London School of Economics (LSE), IZA & CESIfo Sergi Jiménez, Universitat Pompeu Fabra, BSE & FEDEA Juan Oliva, University of Castilla La Mancha & CIBERFES, ISCIII Cristina Vilaplana Prieto, University of Murcia Analía Viola1, FEDEA
June 2026
Abstract
Population ageing is raising demand for long-term care (LTC), and the growing prevalence of cognitive impairment (CI) is one of its key drivers. Clinical evidence estimates that 18.5% of Spaniards aged 65 and over attending primary care have some form of CI, rising to 45.3% among those aged 85 and above. Applying a survey-based threshold, we classify 19.0% of the population aged 65+ as cognitively impaired, close to clinical estimates but strongly graded by educational attainment. Using pooled pre-COVID data from a longitudinal sample of individuals aged 65+, we examine how CI and physical limitations affect health and LTC utilisation and estimate the associated costs and financial burden. We report four findings. First, socioeconomic status at older ages is strongly associated with CI. Second, although both CI and physical limitations increase health and LTC use, physical impairment is linked to higher overall care utilisation (72% versus 50% for CI) and nursing home residence (4.0% versus 3.3%). Third, informal caregiving is the largest component of LTC costs, accounting for 55% of the total. Finally, the replacement cost of informal care would exhaust the entire budget of Spain’s LTC system (SAAD).
Keywords: Cognitive impairment, long-term care, informal care, Spain, ageing, care utilisation. JEL codes: I18, I38, J14
1 We acknowledge financial help from Agencia Estatal de Investigación project PID2023-147602OB-I00. Analía Viola acknowledges the Agencia Estatal de Investigación for financial support JDC2022-049212-I.
1. Introduction
Population ageing is reshaping demand for health and long-term care (LTC) across Europe, posing significant challenges to the sustainability of welfare programs. However, its impact on health and LTC expenditure remains debated, as much of the increase in care needs reflects proximity to death, morbidity, and technological change rather than ageing itself (Zweifel et al., 1999; Zweifel, 2022; Breyer et al., 2010; Costa-Font and Vilaplana-Prieto, 2020). Among the key drivers of age-related care demand is the growing prevalence of cognitive impairment (CI) and neurodegenerative diseases.
Estimating how many people live with CI and neurodegenerative diseases is difficult, largely because of persistent under-diagnosis. Conservative estimates suggest that between 1 and 1.5 million people in Spain may be affected by a neurodegenerative condition, with cognitive impairment present in most cases (Oficina de Ciencia y Tecnología del Congreso de los Diputados, 2023). Within this broader picture, dementia is a particularly pressing public health challenge, affecting an estimated 734,000 to 937,000 people (Ministerio de Sanidad, 2019). Understanding the scale of the problem, including the diverse needs of people with dementia, is therefore essential to designing a sustainable care model for the future. This paper aims to contribute to that understanding.
Alzheimer’s disease accounts for approximately 60-80% of all dementia cases (Ministerio de Sanidad, 2019). The Gómez de Caso study estimates that 18.5% of non-institutionalised primary care attendees aged 65 and older have cognitive impairment (95% CI 17.3-19.7%; Vega Alonso et al., 2018). Prevalence varies by gender (adjusted rates are higher among women), education level, marital status and age, reaching 45.3% among those aged 85 and older (Vega
Alonso et al., 2018). As discussed in Section 4, these clinical estimates are not directly comparable with the survey-based measure used in this chapter, which yields a similar overall share but is strongly influenced by educational attainment.
The growing prevalence of dementia is placing increasing pressure on healthcare and longterm care support systems, pointing to the urgent need for further adaptation to meet the demands of an ageing population. The Spanish Ministry of Health has developed two strategies, namely the so-called “Strategy on neurodegenerative disorders” and the “Comprehensive plan for Alzheimer's and other dementias”2. The principal challenges include the need for an effective diagnosis, early intervention, and access to comprehensive care, all of which are essential to managing dementia effectively3. This includes psychological support, social integration, and the creation of dementiafriendly environments4, which can help maintain a better quality of life while easing the burden placed on families and communities.
This paper draws on the best available evidence to study the prevalence, drivers and costs of dementia and neurodegenerative disorders in Spain. To provide context, we briefly describe the health and long-term care system and the reforms under way. We report four sets of findings. First, socioeconomic status at older ages is strongly associated with CI. Second, although both CI and physical limitations increase health and long-term care use, physical impairment is associated with higher overall care utilisation (72% versus 50% for CI) and nursing home residence (4.0% versus
Ministerio de Sanidad, Servicios Sociales e Igualdad. Estrategia en enfermedades neurodegenerativas del Sistema Nacional de Salud (2016):
https://www.sanidad.gob.es/areas/calidadAsistencial/estrategias/enfermedadesNeurodegenerativas/docs/Est_Neurod egenerativas_APROBADA_C_INTERTERRITORIAL.pdf
2 Ministerio de Sanidad, Consumo y Bienestar Social. Plan integral de Alzheimer y otras demencias. 2019-2023 (2019): https://www.sanidad.gob.es/profesionales/saludPublica/docs/Plan_Integral_Alhzeimer_Octubre_2019.pdf
3 Addressing these challenges, however, entails closer collaboration between medical professionals, caregivers, and policymakers to raise awareness, improve diagnostic tools, and requires funding for both individuals living with dementia and their families.
4 Such environments might include adapting public spaces and homes to better accommodate people with cognitive impairments, as well as training caregivers and healthcare providers in specialized dementia care.
3.3%). Third, informal caregiving is the largest component of long-term care costs, accounting for 55% of the total. Finally, we estimate the monetary value of informal care using the replacement cost method, which prices the hours of informal care at the cost of equivalent formal home care services. Our estimates suggest that fully substituting informal care with formal care would exhaust the entire budget of the Spanish System for Autonomy and Care for Dependency (Sistema para la Autonomía y Atención a la Dependencia, SAAD).
The remainder of the paper is organised as follows. The next section reviews the evidence on the drivers and costs of dementia and neurodegenerative disorders. Section 3 discusses the policy and institutional environment, Section 4 describes the data sources and definitions used, and Section 5 presents the results of our estimates. Section 6 concludes.
2. The Drivers and Costs of Dementia
Ageing effects. Age is best understood as a predisposing factor rather than a need factor in the demand for care services (de Meijer et al., 2013). Its role in driving overall healthcare spending is comparatively minor (Zweifel et al., 1999; Seshamani and Gray, 2004; Carreras et al., 2018; Costa-Font and Vilaplana, 2020; Breyer and Lorenz, 2021; Zweifel, 2022). By contrast, its influence on long-term care (LTC) expenditure remains consistently significant, even after controlling for proximity to death (Hashimoto et al., 2010; Karlsson and Klohn, 2014; Howdon and Rice, 2018). As populations age, demand for LTC services is therefore expected to grow substantially across Europe over the coming decades (European Commission, 2024). A key driver of this growth is the rising prevalence of neurodegenerative diseases, particularly those involving cognitive impairment (Oficina de Ciencia y Tecnología, 2023).
Prevalence. Identifying the exact number of people living with neurodegenerative diseases is difficult, largely due to persistent under-diagnosis, as individuals—especially in the early stages—often do not seek or receive an accurate diagnosis5. Conservative estimates nonetheless suggest that between 1 and 1.5 million people in Spain are affected, most of them with some degree of cognitive impairment. Within this group, dementia is a particularly pressing public health challenge, affecting an estimated 734,000 to 937,000 people. Dementia is not a single disease but an umbrella term for disorders that progressively erode memory, reasoning and daily functioning. Alzheimer’s disease is its leading cause, followed by other significant forms such as vascular dementia and Lewy body dementia.
Costs of dementia. Cost-of-illness studies estimate large social costs of dementia, comparable to those of professional care (Kosaner Kließ et al., 2021; Wimo et al., 2023). A recent study estimates that the average annual cost of care for patients with Alzheimer’s disease (AD) in 2021 ranged from €42,336 to €70,445, rising with the severity of cognitive impairment and doubling between moderate and severe stages (Gómez Maldonado et al., 2024). Healthcare expenses accounted for 5.2% to 8.6% of the total, and formal LTC services provided by professionals for 7.7% to 12.8%. Informal care, typically provided by family members or other unpaid caregivers, was by far the largest component, at 69.0% to 81.4% of the total. These figures illustrate not only the considerable financial burden of dementia on health systems but also the critical role of informal caregivers. This heavy reliance on unpaid care underscores the need for policies that support family caregivers, including financial assistance, respite services and better training to help them manage the demands of caregiving6.
5 This gap reflects persistent stigma around cognitive decline, the subtle onset of symptoms, and the common misconception that memory loss is simply a normal part of ageing. As a result, the actual number of people living with dementia is likely higher than current estimates suggest.
Non-healthcare costs associated with brain damage, including stroke and traumatic brain injury, rise significantly with the severity of functional impairment (Mar et al., 2011). In that study, costs increased from €16,484 for individuals with mild physical or cognitive impairment to €44,550 for those with severe impairment (base year 2008). The composition of these costs also shifts with severity. At mild levels of impairment, informal care, typically provided by family members or friends, accounts for a larger share of the total, reflecting greater reliance on unpaid caregivers at this stage. As impairment worsens, formal care provided by professional services becomes the dominant cost, pointing to a growing need for structured professional support as functional decline progresses and underscoring the mounting financial strain on both families and health systems.
The growing burden of informal care is further illustrated by Vilaplana-Prieto and Oliva-Moreno (2025), who estimated the time spent on informal care for people with Alzheimer’s disease (AD) living at home, and its economic value, comparing 2021 with 2008. Despite the relatively short interval, they found that the number of people with AD living at home rose by 43%, with a corresponding increase in the number receiving informal care. Although several factors likely contribute, the authors identify population ageing as a key driver: between 2008 and 2021, the population aged 65 and over grew by 24.2%, and the population aged 85 and over by 74.4%.
6 The differences between the total cost figures and the weight of the items are due to the shadow price applied to the valuation of the informal care time (home employee vs. home help service).
3. Health and Long-Term Care System
Dementia care in Spain is delivered through a combination of healthcare and social care services, reflecting the institutional separation between the National Health System (NHS) and the long-term care (LTC) system. Diagnosis, clinical management and treatment are provided mainly through the health system, involving primary care physicians, neurologists, geriatricians and memory clinics, although access and availability vary substantially across Autonomous Communities. As dementia progresses and functional dependency increases, care needs fall increasingly within the remit of the LTC system, which provides home care, day centres, residential facilities and caregiver support according to assessed dependency levels. Coordination between the two sectors remains uneven, however, and fragmented responsibilities across adminis trative levels often disrupt continuity of care, particularly for people with complex and evolving needs. Families therefore continue to play a central role, providing substantial unpaid support and acting as the main coordinators of services across both sectors.
While the NHS provides comprehensive medical care, LTC developed outside the health system as a separate pillar of social protection. Responsibility has traditionally been shared between central and regional governments, with services delivered by a mix of public, private and non-profit providers. Like other Southern European countries, Spain has historically had low levels of formal LTC provision relative to Western European peers. Families have instead remained the primary providers of care, reflecting a strongly familialistic welfare model that places responsibility for dependent individuals on household networks rather than public institutions (Costa-Font, 2010; Costa-Font and Vilaplana-Prieto, 2020; Costa-Font et al., 2025).
A major shift came with the Promotion of Personal Autonomy and Care for Dependent Persons Act (Law 39/2006), which created the System for Autonomy and Care for Dependency (Sistema para la Autonomía y Atención a la Dependencia, SAAD) and came into force on 1 January 2007. The reform established a nationwide LTC system based on three principles: the universal and public nature of the right to LTC benefits, equal access according to assessed need, and shared responsibility across levels of government, with private providers allowed to participate in service delivery (Costa-Font et al., 2025, Costa-Font et al, 2026). It was one of the most ambitious expansions of the Spanish welfare state, aiming to reduce reliance on informal family care and create a comprehensive system of publicly supported LTC.
Access to SAAD is universal but conditional on a needs assessment. Applicants are evaluated with the official Dependency Assessment Scale, which classifies them into three levels reflecting the intensity of support required for activities of daily living: Moderate (Degree I), Severe (Degree II) and High Dependency (Degree III). The assessment also considers cognitive impairment, particularly where it limits decision-making and independent functioning, and includes adaptations for people with conditions affecting cognitive capacity. Beneficiaries are entitled to a package of services or cash benefits according to the severity of their needs, including residential care, home care, day-care centres, telecare, and cash allowances for family caregivers or for purchasing care. Financing is shared between the central government, the Autonomous Communities and, for some services, users through income-related co-payments.
However, SAAD’s implementation coincided with the severe economic crisis of 2008- 2014, which constrained public finances and delayed the system’s expansion (Peña-Longobardo et al., 2016). Long waiting lists emerged, with people assessed as eligible waiting extended
periods before receiving services. Faced with these constraints, policymakers increasingly relied on cash benefits supporting informal family care rather than expanding professional services (Costa-Font et al., 2018; Costa-Font et al., 2025).
Since then, the system has grown considerably. By the end of 2024, almost 1.5 million people were receiving support services or cash subsidies (IMSERSO, 2024), and public LTC expenditure now exceeds 1% of GDP (Jiménez-Martín and Viola, 2022). User contributions account for approximately 22% of total SAAD expenditure on average (Montserrat Codorniu, 2024). Recent reforms have focused on strengthening quality standards, raising minimum staffing requirements for public and private providers, and reducing waiting times. Policy has also increasingly prioritised ageing in place by expanding home- and community-based care while improving the quality of both domiciliary and residential services. This reorientation is consistent with broader evidence on the importance of supporting informal caregivers and delaying or avoiding institutionalisation (Ministerio de Derechos Sociales y Agenda 2030, 2022, 2024).
4. Data and Definitions
Sample. Our primary data source is the Survey of Health, Ageing and Retirement in Europe (SHARE). We pool data from Waves 1 (2004/05), 2 (2006/07), 4 (2010/11), 5 (2012/13), 6 (2014/15), and 7 (2016/17), covering the pre-COVID period. Although SHARE surveys individuals aged 50 and over, our analysis is restricted to respondents aged 65 years and older. Cognitive impairment. We define cognitive impairment using a threshold score of 6 or below, following the approach of Crimmins et al. (2011) and Langa et al. (2017). The cognitive indicator combines performance across four domains:
• 10-word immediate recall: immediate recall of a list of 10 words, measuring short-term memory.
• 10-word delayed recall: recall of the same list after a delay, assessing memory consolidation.
• Serial 7s: sequential subtraction of seven from 100, measuring attention and working memory.
• Date naming: correct identification of the current date, capturing temporal orientation.
The maximum possible score is 29 points, although observed scores in our sample range from 0 to 28. Individuals scoring 6 or below are classified as cognitively impaired. To minimise selection bias arising from severe cognitive impairment, we also classify as cognitively impaired those whose interview was completed by a proxy respondent because they were unable to participate due to cognitive limitations. Proxy interviews are identified using the SHARE question that records whether the survey was answered on behalf of the respondent.
Comparison with external prevalence estimates. Applying this definition, 19.0% of the population aged 65 and over is classified as cognitively impaired (Table 1). This figure should not be read as the clinical prevalence of cognitive impairment. In the classification of Crimmins et al. (2011) and Langa et al. (2017), on which our threshold is based, scores of 6 or below identify dementia-level impairment in the US Health and Retirement Study, while milder impairment without dementia corresponds to higher scores (7-11 on their 27-point scale). Applied to Spanish cohorts aged 65 and over, many of whom did not complete primary education, the same cut-off classifies a larger share of the population, because performance in word recall and serial subtraction depends strongly on schooling. In our sample, the unweighted share scoring 6 or below falls from 31.1% among respondents who did not complete primary education to 14.9% among those with primary education, 5.3% among those with secondary education and 4.7% among those with tertiary education. Our estimate therefore exceeds the 734,000-937,000 people estimated to be living with dementia in Spain (Section 2), because our measure captures both dementia-level impairment and milder impairment among less educated respondents. For this reason, the fully adjusted specifications in Section 5 control for educational attainment.
Our estimate is very close to the figure most often cited for Spain: 18.5% (95% confidence interval 17.3-19.7%; 18.7% after adjusting for the population size of each region), from the Gómez de Caso study (Vega Alonso et al., 2018). That study combined previously known cases with cases confirmed during the study among 4,624 patients aged 65 and over who attended 179 sentinel family physicians or nurses on four randomly selected days in five regional Health Sentinel Networks. Besides using a clinical rather than a survey-based definition, it covers only the noninstitutionalised population attending primary care. SHARE, by contrast, samples the communitydwelling population and partially captures institutional care: respondents interviewed at home in one wave remain in the panel if they move to a nursing home in a later wave, and temporary nursing home stays are also recorded (see Section 5). This difference in coverage would, if anything, raise the SHARE-based estimate, so the similarity of the two figures partly reflects offsetting differences in definition and coverage rather than a common measure. Self-reported and screening measures yield higher figures. In the 2017 Spanish National Health Survey (ENSE), 31.3% of non-institutionalised individuals aged 65 and over report some difficulty remembering or concentrating (Ministerio de Sanidad, Consumo y Bienestar Social, 2018), and a communitypharmacy study based on a convenience sample of 910 caregivers and older relatives found that 38.5% of the older participants were at risk of cognitive impairment (SEFAC and Neuraxpharm, 2023). These comparisons suggest that, in the aggregate, our measure does not overstate cognitive impairment: it lies close to clinical estimates and well below self-reported measures, although, as noted above, it is strongly graded by education.
Cost estimation
Cost estimation follows the methodology of Costa-Font et al. (2025). Formal care is valued using official sources on the cost of public services, and informal care using the replacement cost method.
5. Results
Cognitive score and limitations. We begin by examining the distribution of cognitive scores (Figure 1a), using a score of 6 or below as the threshold for cognitive impairment. The dashed vertical lines mark the 6th, 20th, 40th, 60th and 80th percentiles (4, 7, 10, 13 and 16 points). Most respondents retain relatively good cognitive functioning: six in ten score between 8 and 17 points, and the distribution has a long left tail of low scores. The impairment threshold lies within the bottom quintile (the 20th percentile is 7 points), so that 19.0% of individuals aged 65 and over score 6 or below. A sizeable share of the older population therefore shows relatively low cognitive functioning.
Figure 1b shows the distribution separately for people aged 65-84 and those aged 85 and over. It reveals a pronounced age gradient, with the distribution shifting towards lower scores among the oldest respondents. Specifically, 85.2% of those aged 85 and over score 12 or less, compared with 50.2% of those aged 65-84, and 48.1% score 6 or below, compared with 14.0%. The figure for the oldest group is close to the clinical estimate of 45.3% for people aged 85 and over (Vega Alonso et al., 2018). The share of interviews answered by a proxy also rises sharply with age, from 4.8% to 23.2%. These findings are consistent with the well-established association between advancing age and cognitive decline and show a marked concentration of the oldest-old at the lower end of the distribution.
[Insert Figures 1a and 1b about here]
Physical limitations. Physical limitations are measured using difficulties with activities of daily living (ADLs), a standard indicator of functional capacity among older adults. The ADLs considered are dressing, bathing or showering, eating, walking across a room, getting in and out of bed, and using the toilet. Following the clinical literature, an individual is classified as having a physical limitation if they report difficulty with two or more of these activities. This threshold captures moderate to severe functional impairment that is likely to require assistance with everyday living.
Figure 2a shows the distribution of ADL limitations in the SHARE sample. It is heavily concentrated at zero: most respondents aged 65 and over report no difficulty with basic daily activities. The proportion declines sharply as the number of limitations rises, with a slight increase at five and six limitations, so severe physical disability is relatively uncommon in the older population. A non-negligible minority nonetheless report multiple limitations.
Figure 2b compares the distribution for respondents aged 65-84 and those aged 85 and over and shows a pronounced age gradient in functional ability. About 85% of those aged 65-84 report no limitations, against around 56% of those aged 85 and over. Only 8.3% of respondents aged 65- 84 report difficulty with two or more ADLs, compared with 32.0% of those aged 85 and over, almost four times as many.
[Insert Figures 2a and 2b about here]
These distributions show a marked decline in physical functioning at advanced ages. Although most people entering older age remain physically independent, the likelihood of limitations in essential daily activities rises sharply among the oldest-old. This is consistent with the well-established age-related increase in frailty and disability, and points to growing demand for long-term care and support services as populations age. It also shows why functional limitations should be considered alongside cognitive impairment when assessing dependency and the demand for LTC.
Care utilisation and outcomes. Figure 3 shows the proportion of people aged 65 and over receiving long-term care (LTC), by group of the cognitive score distribution. We distinguish three non-mutually exclusive forms of care: informal care at home, formal care at home, and residential care in a nursing home. This allows us to examine how the use of each type varies with cognitive functioning.
Informal care is the most common form of support: about 17% of older adults receive help at home from family members, friends or other unpaid caregivers. Formal home care, provided by professional caregivers or care agencies, is used by 12.9% of respondents, while residential care is comparatively uncommon, with only 1.6% of the sample living in a nursing home. A clear gradient emerges across cognitive score groups. Among respondents scoring 0-4, 38.1% receive informal care and 29.6% formal home care, compared with 8.6% and 6.8% of those scoring 14 or more. Nursing home residence, though rare overall, also rises as scores fall: 8.2% among those scoring 0-4, against 0.2% among those scoring 14 or more. Lower cognitive functioning is therefore associated with a higher probability of receiving each type of LTC, although the size of the increase differs by type.
These descriptive patterns show that lower cognitive function is associated with a higher probability of receiving LTC, particularly care provided in the community. The much higher prevalence of home-based than institutional care also points to the central role of ageing in place (Costa-Font et al., 2009; Costa-Font and Vilaplana-Prieto, 2022) and the continued importance of family caregiving in meeting older adults’ care needs.
[Insert Figure 3 about here]
Turning to the effect of CI on nursing home care, it is worth noting that SHARE data do not provide a complete cross-sectional picture of all older adults in nursing homes7. Our sample captures only a subset of nursing home users and probably understates the overall prevalence of residence. However, the longitudinal structure of SHARE offers information on transitions into institutional care and, importantly, on barriers to access. Among respondents who moved into residential care, those with cognitive impairment report substantially greater unmet need than those with physical limitations. Specifically, 33.3% of respondents with CI report being unable to access a nursing home because of financial constraints, compared with only 7.6% of those with physical limitations. Likewise, 50.0% of those with CI report difficulties because of a lack of available places, compared with just 5.2% of those with physical limitations. These findings suggest that cognitive impairment is associated with greater barriers to institutional care, in terms of both affordability and availability.
Taken together, the descriptive evidence shows how LTC use varies with cognitive functioning. People with lower cognitive scores are substantially more likely to receive both informal and formal care, while those with the highest scores make little use of LTC services. The evidence on nursing home access further suggests that, despite their greater care needs, older adults with CI face significant obstacles in obtaining residential care.
7 We identify two main groups of nursing home users: (i) individuals reporting temporary stays in a nursing home, and (ii) permanent residents who were interviewed while living in the community in a previous SHARE wave but subsequently moved into a nursing home.
The interaction between cognitive score and limitations. Table 1 reports the joint distribution of physical limitations and CI among people aged 65 and over. Overall, 80.6% of respondents report no ADL limitations, and 88.2% report fewer than two, so are not classified as physically limited. About 75% report neither physical limitations nor cognitive impairment, so most older adults remain relatively independent. Around 12% report physical limitations (two or more ADL difficulties) and 19.0% are classified as cognitively impaired. About 5.9% have both, roughly one third of those with CI and half of those with physical limitations, which shows a substantial overlap between physical and cognitive decline at older ages.
[Insert Tables 1, 2a and 2b about here]
Table 2a compares the sociodemographic characteristics of three mutually exclusive groups: (i) no impairment (0-1 ADL limitations and a cognitive score of 7 or above); (ii) physical impairment only (two or more ADL limitations and a cognitive score of 7 or above); and (iii) cognitive impairment (a cognitive score of 6 or below, irrespective of physical limitations). Several patterns emerge.
First, there is a pronounced age gradient. People without impairments are 74 years old on average, compared with 80 among those with physical impairment and 82 among those with cognitive impairment. This is consistent with the earlier descriptive evidence that both forms of impairment become more prevalent with age.
Second, the groups differ markedly in socioeconomic characteristics. Those without impairments are more likely to be married or living with a partner and have substantially higher educational attainment. They are about four percentage points more likely to have completed tertiary education than those with physical impairment, and six points more likely than those with cognitive impairment. The gap is larger at the bottom of the educational distribution: 50.3% of the cognitively impaired group did not complete primary education, compared with 24.4% of those without impairments. These differences are consistent with evidence linking education to healthier ageing and greater cognitive reserve.
Income and wealth also differ substantially. Average annual income per capita is €13,733 among those without impairments, compared with €9,906 among those with cognitive impairment. The wealth gap is larger still: average per capita wealth is €189,918 among the nonimpaired but €146,653 among the cognitively impaired, a difference of more than €43,000. These findings point to a strong socioeconomic gradient in both physical and cognitive health at older ages.
Table 2b compares health status, care needs and LTC utilisation across the same groups. Cognitive scores differ sharply, as expected: the average is 13.53 among those without impairments and 10.53 among those with physical impairment only, but just 4.06 among the cognitively impaired.
Functional limitations also vary considerably. Respondents with physical impairment report substantially more ADL and instrumental ADL (IADL) limitations than those with cognitive impairment, especially for ADLs. This follows from the definition of the physical impairment group, which is based on significant functional disability, whereas cognitive impairment can occur without severe physical limitations.
These differences carry over to care utilisation. The share receiving any LTC rises markedly with impairment: 15% of respondents without impairments, 50% of those with cognitive impairment and 72% of those with physical impairment. Although both conditions substantially raise the need for support, physical limitations are therefore associated with considerably higher rates of care use.
The type and intensity of care also differ. Nursing home residence is uncommon in every group but highest among those with physical impairment (4.0%), followed by those with cognitive impairment (3.3%), and lowest among those without impairments. People with physical impairment also receive more care at home. Among recipients, they receive an average of 84 hours of informal care per month, compared with 69 hours for those with cognitive impairment, and 33 and 29 hours of formal home care, respectively.
Overall, both cognitive and physical impairment are associated with substantially higher LTC use, but in different ways. Physical limitations are associated with higher levels of both formal and informal care. Individuals with cognitive impairment use comparatively less homebased and institutional care despite substantial care needs. This may reflect differences in the type of care required, but it may also reflect unmet need and barriers to formal services, particularly residential care, as the descriptive evidence above suggests.
Examining long-term care use and determinants. We first examine the determinants of receiving any LTC and then distinguish its main components: formal home care, informal home care and nursing home care. To capture both the extensive and intensive margins, we estimate models for the probability of receiving each type of care and, conditional on receipt, the hours of formal and informal care received in the previous month. The fully adjusted specifications include indicators for physical and cognitive impairment, age and age squared, marital status, gender, a gender-by-marital status interaction, whether the respondent has children and how many, educational attainment, and income and wealth. This allows us to isolate the association between impairment and care use while accounting for observable differences in family structure and socioeconomic resources that also influence access to care.
Table 3 reports linear probability estimates of the association between physical and cognitive impairment and the receipt of any LTC. The unconditional estimates in Column (1) show that both impairments are associated with a substantially higher probability of receiving care, and the association is considerably larger for physical limitations. Adding age and age squared in Column (2) reduces both coefficients, indicating that part of the relationship reflects the higher prevalence of impairment at older ages. Impairment nonetheless remains strongly associated with care receipt, so the relationship is not driven by age alone.
[Insert Table 3 about here]
The fully adjusted specification in Column (3) confirms these findings after controlling for socioeconomic and family characteristics. Marital status emerges as an important determinant of care utilisation. Being married is associated with a reduction of approximately 8 percentage points (pp) in the probability of receiving care among men, while the positive interaction term indicates that this reduction is around 4.6 pp smaller among women. These results are consistent with gender differences in caregiving arrangements and household support networks. Educational attainment also plays a role. Compared with individuals who did not complete primary education, those with primary education are approximately 3.8 pp less likely to receive care, whereas the differences for individuals with high school or tertiary education are small and statistically insignificant. Overall, the results indicate that although demographic and socioeconomic characteristics explain part of the variation in care use, impairment status remains a key determinant of receiving long-term care.
Tables 4a and 4b examine the use of formal home care. Across all specifications, both cognitive and physical impairments are positively and significantly associated with the
probability of receiving professional home care. Consistent with Table 3, the estimated coefficients decline somewhat after progressively adding controls, suggesting that part of the raw association reflects differences in age and socioeconomic characteristics. However, the effects remain sizeable and statistically significant throughout.
[Insert Tables 4a and 4b about here]
The results also reveal important socioeconomic differences in access to formal care. Marital status matters mainly on the extensive margin: married respondents are about 5 pp less likely to receive formal home care, pointing to the continuing importance of spouses as informal caregivers, while the additional effect for married women is small and only marginally significant. Conditional on receiving formal care, marital status is not significantly associated with the number of hours. In contrast, educational attainment is positively associated with the use of formal services. Relative to respondents with less than primary education, individuals with a high school education are approximately 4.5 pp more likely to receive formal home care, while those with tertiary education are around 4.9 pp more likely to have access to formal care. These findings suggest that more educated individuals may be better able to navigate the LTC system or have greater resources to complement publicly funded services.
Conditional on receiving formal care, both physical and cognitive impairments are associated with a significantly greater number of care hours. The estimated effects are substantially larger for individuals with physical limitations, indicating that functional disability is a particularly important determinant of care intensity. Age also displays a nonlinear relationship with formal care use: while the linear age term is negative, the positive coefficient on age squared suggests that formal care use increases again at very advanced ages.
To complete the picture, Tables 5a and 5b focus on informal home care. Consistently, both physical and cognitive impairments substantially increase the probability of receiving unpaid assistance from relatives or friends. Although the estimated effects become smaller after controlling for demographic and socioeconomic characteristics, they remain highly significant, indicating that impairment independently predicts informal caregiving.
Family characteristics appear to play a more prominent role in informal than in formal care arrangements. Married women are more likely than married men to receive informal care, consistent with the availability of family support within the household (Costa-Font et al., 2025), although this difference is significant only at the 10% level. In contrast to formal care, educational attainment is negatively associated with informal care use, suggesting that individuals with lower levels of education rely more heavily on family caregivers, possibly reflecting differences in financial resources or access to formal services.
[Insert Tables 5a and 5b about here]
Conditional on receiving any informal care, both physically and cognitively impaired respondents receive substantially more hours of care than individuals without impairments. Once again, the effects are considerably larger for those with physical limitations, highlighting the greater time demands associated with assisting individuals experiencing functional disability. These findings reinforce the central role played by family caregivers in supporting older adults with physical impairments.
Finally, Table 6 examines the impact of cognitive and physical impairment on nursing home care access8. Our estimates indicate that physical limitations are more strongly associated with nursing home use than cognitive impairment. Individuals with physical impairments are approximately two percentage points more likely to reside in a nursing home, whereas the corresponding increase associated with cognitive impairment is only around 1.1 percentage points (Table 6, Column 1). Although these probabilities remain relatively small, they are consistent with the descriptive evidence showing that institutional care is comparatively uncommon in Spain and that most long-term care continues to be provided in the community. Together with the earlier findings on unmet need, these results suggest that barriers to accessing residential care may be particularly important for older adults with cognitive impairment, who appear to rely disproportionately on home-based and family care despite having substantial care needs.
[Insert Table 6 about here]
Cost estimation. Table 7 reports the estimated costs of long-term care at both the individual and aggregate levels. The costing methodology follows the approach developed in Costa-Font et al. (2025), combining information on service utilisation with unit costs to estimate the economic value of formal and informal care across different impairment groups.
[Insert Table 7 about here]
The results reveal substantial variation in the cost of care according to individuals' health status. Average annual long-term care costs per user amount to €2,485 for individuals with no significant impairments (0–1 ADL limitations and a cognitive score of 7 or above), €9,963 for those with physical impairment only (two or more ADL limitations and a cognitive score of 7 or above), and €16,893 for individuals with cognitive impairment (cognitive score between 0 and 6, irrespective of ADL limitations). Thus, the average cost of caring for an individual with cognitive impairment is almost seven times higher than that for an older adult without significant impairments and about 70% higher than the cost associated with physical impairment alone.
8 Because SHARE identifies only a subset of institutionalized individuals, the number of nursing home residents in the estimation sample is small, and the results should therefore be interpreted with caution.
Disaggregating these estimates by type of care highlights the different sources of expenditure. Average annual expenditure on formal home care amounts to €751 per user in the non-impaired group, €1,808 among individuals with physical impairments, and €4,517 for those with cognitive impairment. A similar pattern emerges for informal care. The estimated value of informal care reaches €2,678, €6,444, and €16,097 per user, respectively, indicating that unpaid family care constitutes the largest component of total care costs among individuals without significant impairments and those with cognitive impairment. Estimated annual costs associated with nursing home care are €4,941 for the non-impaired group, €11,891 for individuals with physical impairments, and €29,703 for those with cognitive impairment, reflecting the high resource intensity of institutional care among the relatively small number of users.
At the aggregate level, the estimated annual cost of long-term care in Spain amounts to €21.2 billion. Informal care accounts for the largest share of expenditure, representing €11.6 billion, or approximately 55% of total LTC costs. This finding points to the central role played by unpaid family caregivers within the Spanish long-term care system. Despite the expansion of publicly funded LTC after SAAD, the economic burden of caring for older adults continues to fall predominantly on families. The particularly high costs associated with cognitive impairment further suggest that population ageing and, as long as highly effective preventive interventions and treatments remain unavailable, the expected increase in dementia prevalence are likely to place growing pressure on both households and the long-term care system in the coming decades.
6. Conclusions
Population ageing is rapidly increasing the demand for health and long-term care (LTC) in Spain, and cognitive impairment (CI), more than ageing alone, is becoming one of its main drivers. Using pooled pre-pandemic SHARE data (2004-2017), this paper estimates the prevalence of CI, its overlap with physical limitations, patterns of LTC use, and the associated economic costs.
Using a survey-based threshold, we classify 19.0% of Spaniards aged 65 and over as cognitively impaired, rising to 48.1% among those aged 85 and over. These figures are close to clinical estimates of 18.5% among primary care attendees aged 65 and over and 45.3% among those aged 85 and over (Vega Alonso et al., 2018), although our measure is strongly graded by education. Physical limitations also rise sharply with age, and about 5.9% of older adults have both cognitive and physical impairments. Both conditions increase the demand for care, but physical limitations are associated with substantially greater use of formal and informal home care: people with physical impairments are 54.7 percentage points (pp) more likely to receive care than those without impairments, compared with 33.2 pp for those with CI. At the same time, people with CI face greater barriers to nursing home care, which suggests unmet need despite the expansion of the System for Autonomy and Care for Dependency (SAAD).
The analysis also reveals a marked socioeconomic gradient. Older adults with CI have lower education, income and wealth than those without impairments, which points to a close link between dependency and socioeconomic disadvantage. Average annual LTC costs per user are €2,485 for people without significant impairments, €9,963 for those with physical limitations and €16,893 for those with CI. At the national level, total LTC expenditure is estimated at €21.2 billion, of which €11.6 billion (55%) is informal care. Finally, using the replacement cost method, we estimate that replacing all informal care with equivalent formal home care would require resources broadly equal to the entire annual budget of SAAD, the main public LTC programme, in place since 2007. This shows how heavily the Spanish LTC system still depends on unpaid family caregivers.
References
- Breyer, F. and Lorenz, N. (2021) 'The "red herring" after 20 years: Ageing and health care expenditures', European Journal of Health Economics, 22, pp. 661–667. https://doi.org/10.1007/s10198-020-01203-x.
- Breyer, F., Costa-Font, J. and Felder, S. (2010) 'Ageing, health, and health care', Oxford Review of Economic Policy, 26(4), pp. 674–690.
- Carreras, M., Ibern, P. and Inoriza, J.M. (2018) 'Ageing and healthcare expenditures: Exploring the role of individual health status', Health Economics, 27(5), pp. 865–876.
- Costa-Font, J. (2010) 'Devolution, diversity and welfare reform: Long-term care in the Latin Rim', Social Policy & Administration, 44(4), pp. 481–494.
- Costa-Font, J., Elvira, D. and Mascarilla-Miró, O. (2009) 'Ageing in place? Exploring elderly people's housing preferences in Spain', Urban Studies, 46(2), pp. 295–316.
- Costa-Font, J., Jiménez-Martín, S., and Vilaplana-Prieto, C. (2026). Returns to caring? Health and wellbeing effects of subsidized long-term care. Journal of Policy Analysis and Management, forthcoming
- Costa-Font, J., Jiménez-Martín, S. and Vilaplana-Prieto, C. (2018) 'Does long-term care subsidization reduce hospital admissions and utilization?', Journal of Health Economics, 58, pp. 43–66.
- Costa-Font, J., Jiménez-Martín, S., Vilaplana Prieto, C. and Viola, A. (2025) 'Universalizing the access to long-term care: Evidence from Spain', in Long-Term Care around the World. Chicago: University of Chicago Press for the National Bureau of Economic Research.
- Costa-Font, J. and Vilaplana-Prieto, C. (2020) 'More than one red herring? Heterogeneous effects of ageing on health care utilisation', Health Economics, 29(S1), pp. 8–29. https://doi.org/10.1002/hec.4035.
- Costa-Font, J. and Vilaplana-Prieto, C. (2022) 'Health shocks and housing downsizing: How persistent is ageing in place?', Journal of Economic Behavior & Organization, 204, pp. 490–508.
- Crimmins, E., Kim, J., Langa, K. and Weir, D. (2011) 'Assessment of cognition using surveys and neuropsychological assessment: The Health and Retirement Study and the Aging, Demographics, and Memory Study', The Journals of Gerontology: Series B, 66(Suppl. 1), pp. i162–i171.
- de Meijer, C., Wouterse, B., Polder, J. et al. (2013) 'The effect of population aging on health expenditure growth: A critical review', European Journal of Ageing, 10, pp. 353–361. https://doi.org/10.1007/s10433-013-0280-x.
- European Commission, Directorate-General for Economic and Financial Affairs (2024) The 2024 Ageing Report: Economic and Budgetary Projections for the EU Member States (2022–2070). Institutional Paper 279. Luxembourg: Publications Office of the European Union.
- Gómez Maldonado, L., de Mora-Figueroa, R., López-Angarita, A., Maravilla-Herrera, P. and Merino, M. (2024) 'Cost of patients with Alzheimer's disease in Spain according to disease severity', Pharmacoeconomics Open, 8(1), pp. 103–114.
- Hashimoto, H., Horiguchi, H. and Matsuda, S. (2010) 'Micro data analysis of medical and longterm care utilization among the elderly in Japan', International Journal of Environmental Research and Public Health, 7(8), pp. 3022–3037.
- Howdon, D. and Rice, N. (2018) 'Health care expenditures, age, proximity to death and morbidity: Implications for an ageing population', Journal of Health Economics, 57, pp. 60–74. https://doi.org/10.1016/j.jhealeco.2017.11.001.
- IMSERSO-Instituo de Mayores y Servicios Sociales. Evolución de los principales indicadores de la gestión del SAAD. Available at: https://imserso.es/autonomia-personaldependencia/sistema-autonomia-atencion-dependencia-saad/evolucion-de-losprincipales-indicadores-de-la-gestion-del-saad
- Jiménez-Martín, S. and Viola, A. (2022) Observatorio de Dependencia. Cuarto Informe. FEDEA Studies on the Spanish Economy, eee2022-16.
- Karlsson, M. and Klohn, F. (2014) 'Testing the red herring hypothesis on an aggregated level: Ageing, time-to-death and care costs for older people in Sweden', European Journal of Health Economics, 15(5), pp. 533–551.
- Kosaner Kließ, M., Martins, R. and Connolly, M.P. (2021) 'Major cost drivers in assessing the economic burden of Alzheimer's disease: A structured, rapid review', Journal of Prevention of Alzheimer's Disease, 8(3), pp. 362–370.
- Langa, K., Larson, E., Crimmins, E., Faul, J., Levine, D., Kabeto, M. and Weir, D. (2017) 'A comparison of the prevalence of dementia in the United States in 2000 and 2012', JAMA Internal Medicine, 177(1), pp. 51–58.
- Mar, J., Arrospide, A., Begiristain, J.M., Larrañaga, I., Elosegui, E. and Oliva-Moreno, J. (2011) 'The impact of acquired brain damage in terms of epidemiology, economics and loss in quality of life', BMC Neurology, 11, Article 46.
- Ministerio de Derechos Sociales y Agenda 2030 (2022) Acuerdo sobre criterios comunes de acreditación y calidad de los centros y servicios del Sistema para la Autonomía y Atención a la Dependencia (SAAD). Madrid.
- Ministerio de Derechos Sociales, Consumo y Agenda 2030 (2024) Estrategia estatal para un nuevo modelo de cuidados en la comunidad: Un proceso de desinstitucionalización (2024–2030). Madrid.
- Ministerio de Sanidad (2019) Plan Integral de Alzheimer y otras Demencias 2019–2023. Madrid.
- Ministerio de Sanidad, Consumo y Bienestar Social (2018) Encuesta Nacional de Salud. España 2017. Serie informes monográficos #1: Salud mental. Madrid: Ministerio de Sanidad, Consumo y Bienestar Social.
- Ministerio de Sanidad, Servicios Sociales e Igualdad (2016) Estrategia en Enfermedades Neurodegenerativas del Sistema Nacional de Salud. Madrid.
- Montserrat Codorniu, J. (2024) 'La coparticipación en la financiación de la atención a la dependencia: Impacto en la sostenibilidad del SAAD', Actas de Coordinación Sociosanitaria, 34, pp. 48–79.
- O'Donovan, J. et al. (2023) 'Validation of a harmonised, three-item cognitive screening instrument for the Survey of Health, Ageing and Retirement in Europe (SHARE-Cog)', International Journal of Environmental Research and Public Health, 20(19), Article 6869.
- OECD (2005) Long-term Care for Older People. Paris: OECD Publishing.
- Oficina de Ciencia y Tecnología del Congreso de los Diputados (2023) Avances en enfermedades neurodegenerativas. Informe C. https://doi.org/10.57952/z6b7-9227.
- Peña-Longobardo, L., Oliva-Moreno, J., García-Armesto, S. et al. (2016) 'The Spanish long-term care system in transition: Ten years since the 2006 Dependency Act', Health Policy, 120, pp. 1177–1182.
- Seshamani, M. and Gray, A. (2004) 'A longitudinal study of the effects of age and time to death on hospital costs', Journal of Health Economics, 23(2), pp. 217–235.
- SEFAC (Sociedad Española de Farmacia Clínica, Familiar y Comunitaria) and Neuraxpharm (2023) Estudio NeuraxCare: Detección precoz del deterioro cognitivo en personas mayores en la farmacia comunitaria. Neuraxpharm España.
- Vega Alonso, T., Miralles Espí, M., Mangas Reina, J.M. et al. (2018) 'Prevalence of cognitive impairment in Spain: The Gómez de Caso study in health sentinel networks', Neurología (English Edition), 33(8), pp. 491–498.
- Vilaplana-Prieto, C. and Oliva-Moreno, J. (2025) 'Time value of informal care of people with Alzheimer's disease in Spain: A population-based analysis', European Journal of Health Economics, 26(3), pp 377-402 https://doi.org/10.1007/s10198-024-01713-y.
- Wimo, A., Seeher, K., Cataldi, R. et al. (2023) 'The worldwide costs of dementia in 2019', Alzheimer's & Dementia, 19(7), pp. 2865–2873.
- Zweifel, P. (2022) 'The "red herring" hypothesis: Some theory and new evidence', Healthcare, 10(2), Article 211.
- Zweifel, P., Felder, S. and Meiers, M. (1999) 'Ageing of population and health care expenditure: A red herring?', Health Economics, 8(6), pp. 485–496.
Figure 1a. Histogram of cognition scores (including proxies). Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Weighted percentages; scores of 25–28 (0.2% of the sample) not shown. The Proxy bar shows the share of interviews answered by a proxy respondent; these respondents are also included in the score bars. Dashed lines mark the 6th, 20th, 40th, 60th and 80th percentiles.
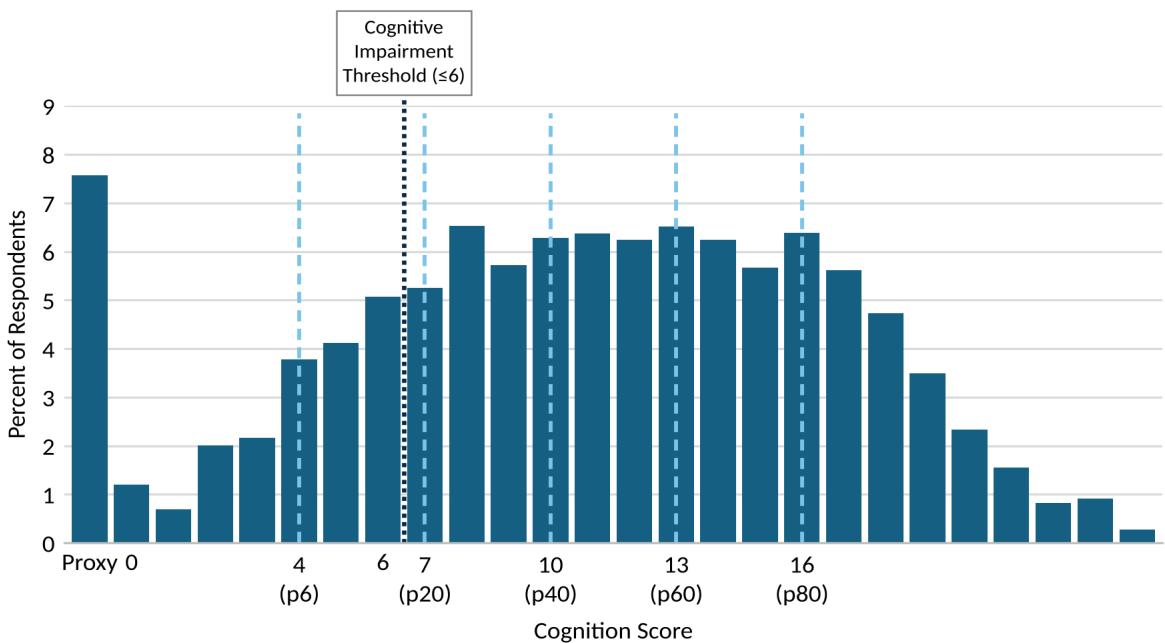
Figure 1b. Histogram of cognition scores by age categories
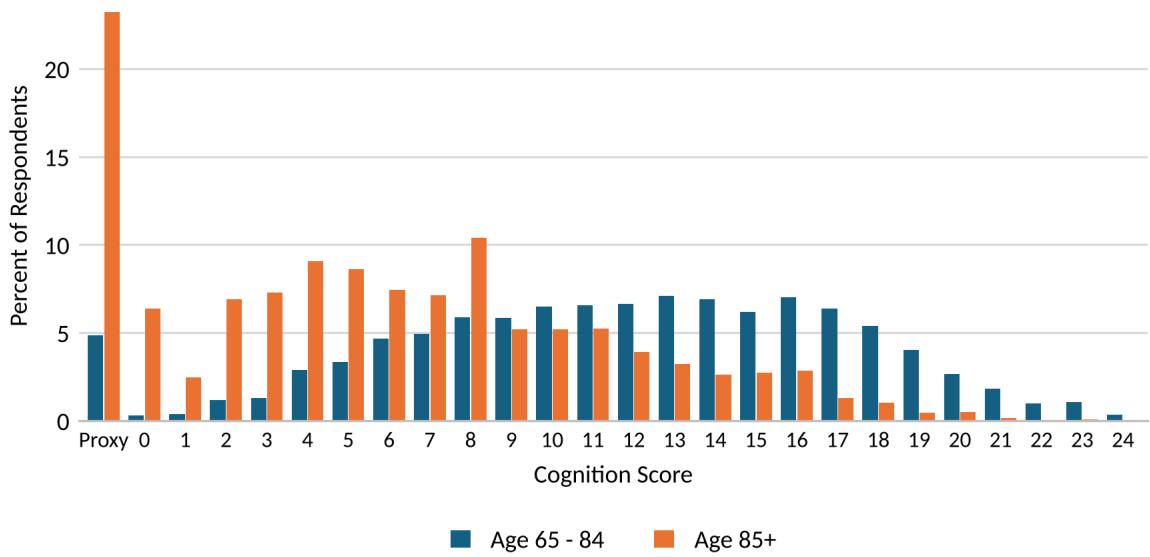
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Weighted percentages within each age group. The Proxy bar shows the share of interviews answered by a proxy respondent; these respondents are also included in the score bars.
Figure 2a. Histogram of ADL limitations Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Weighted percentages.
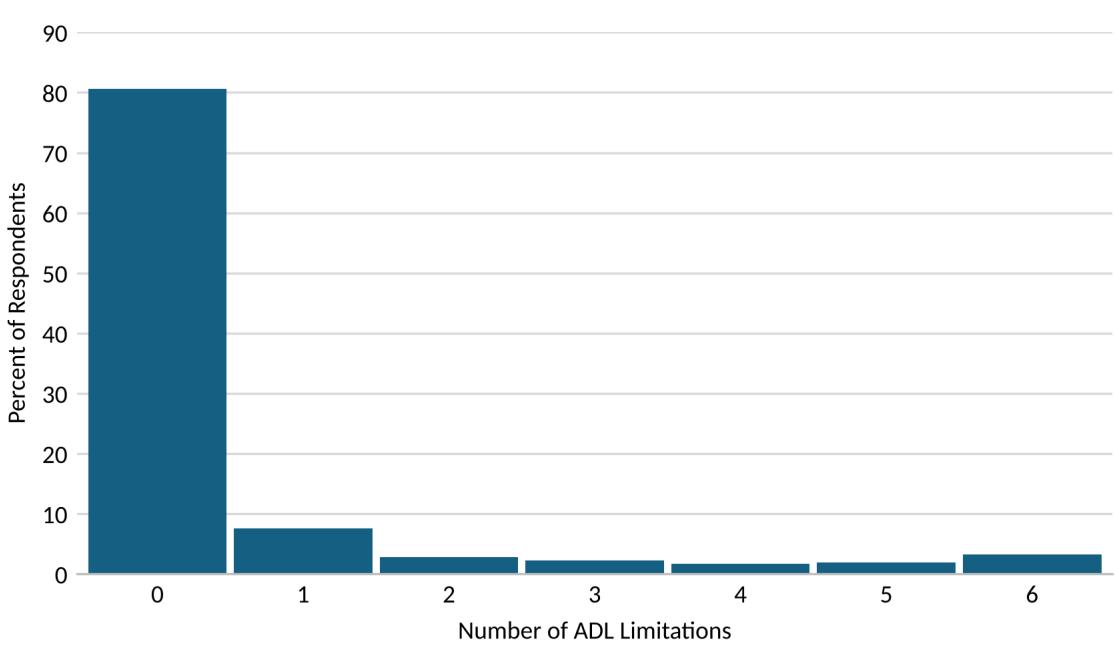
Figure 2b. Histogram of ADL limitations by age categories
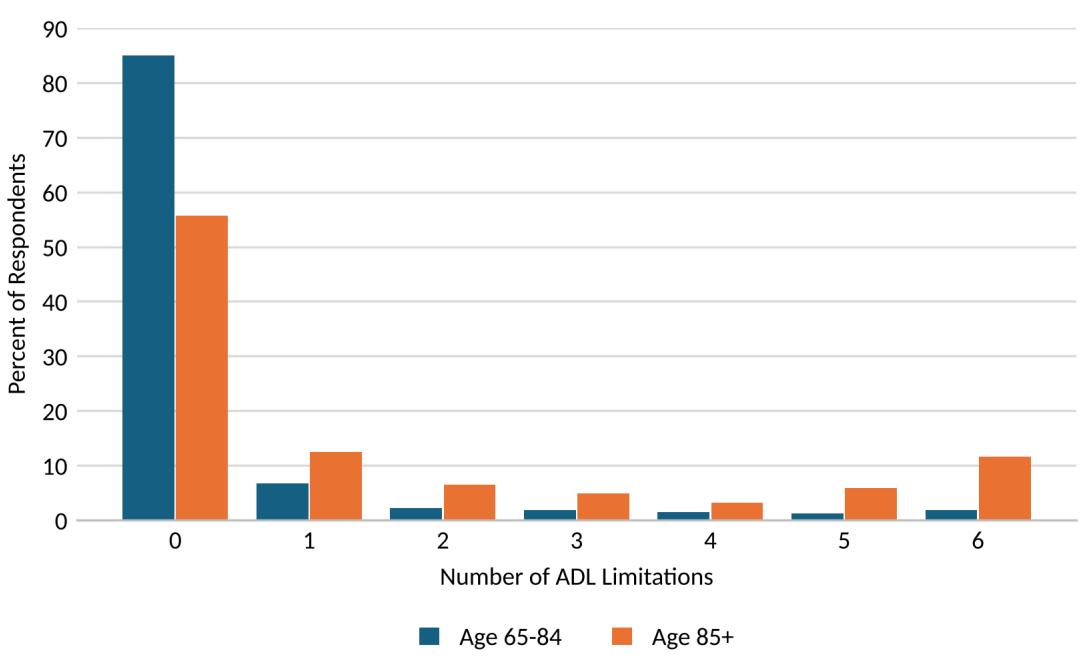
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Weighted percentages within each age group.
Figure 3. Share Receiving Each Type of Care by Cognition Score Group
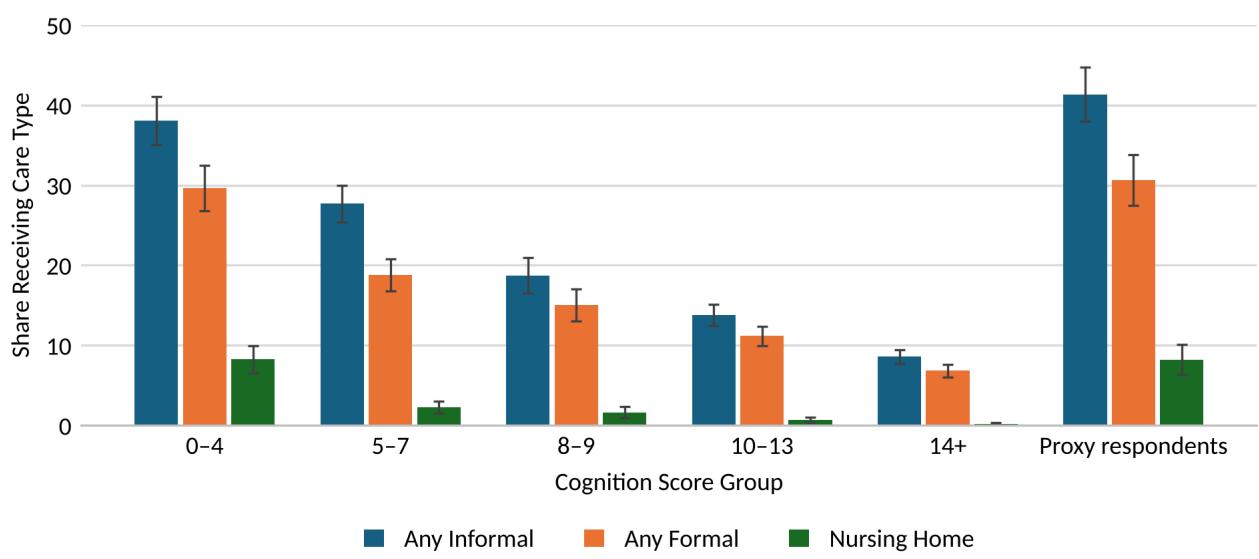
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Weighted shares (%). Error bars show 95% confidence intervals. Proxy respondents are also included in the score groups.
Table 1: Joint distribution of cognition score and ADL limitations
| Limitations | Cognition score 0–6 | Cognition score 7+ | Total |
| 0 ADLs | 10.96% | 69.66% | 80.62% |
| 1 ADL | 2.17% | 5.40% | 7.57% |
| 2+ ADL | 5.86% | 5.95% | 11.81% |
| Total | 18.99% | 81.01% | 100.00% |
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Percentages weighted with SHARE sampling weights. Proxy respondents identified as cognitively impaired are grouped with respondents who scored 0–6 on the cognitive assessment.
Table 2a: Sociodemographic characteristics by cognition score and ADL limitations
| Means | 0 – 1 ADLs & Score 7+ | 2+ ADLs & Score 7+ | Score 0 – 6 (All ADLs) | Total |
| Age | 74.148 | 79.626** | 81.799** | 75.869 |
| 6.647 | 7.872 | 7.153 | 7.483 | |
| Female (0 or 1) | 0.509 | 0.628** | 0.645** | 0.541 |
| 0.500 | 0.484 | 0.479 | 0.498 | |
| Married (0 or 1) | 0.773 | 0.607** | 0.581** | 0.728 |
| 0.419 | 0.489 | 0.493 | 0.445 | |
| Any children (0 or 1) | 0.654 | 0.675 | 0.665 | 0.657 |
| 0.476 | 0.469 | 0.472 | 0.475 | |
| Number of children | 1.781 | 2.142** | 1.922** | 1.827 |
| 1.742 | 2.115 | 1.914 | 1.799 | |
| Primary education (0 or 1) | 0.610 | 0.553** | 0.465** | 0.580 |
| 0.488 | 0.498 | 0.499 | 0.494 | |
| High school (0 or 1) | 0.067 | 0.033** | 0.016** | 0.055 |
| 0.249 | 0.180 | 0.124 | 0.229 | |
| College or more (0 or 1) | 0.079 | 0.037** | 0.017** | 0.065 |
| 0.270 | 0.189 | 0.128 | 0.247 | |
| Work for pay (0 or 1) | 0.029 | 0.019 | 0.005** | 0.024 |
| 0.167 | 0.138 | 0.072 | 0.153 | |
| Income per capita (mean) | 13,733.34 | 11,388.69** | 9,905.89** | 12,904.11 |
| 14,215.67 | 7,388.82 | 5,956.73 | 12,875.45 | |
| Income per capita (median) | 11,224.87 | 9,550.96 | 8,984.38 | 10,630.26 |
| Wealth per capita (mean) | 189,918.10 | 137,858.80** | 146,653.30** | 179,141.50 |
| 338,897.20 | 277,694.80 | 391,396.50 | 346,622.50 | |
| Wealth per capita (median) | 122,837.60 | 85,085.56 | 95,474.23 | 116,486.30 |
| N | 7,830 | 570 | 1,911 | 10,311 |
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Notes: Standard deviations are in italics. Stars indicate rejection of the null hypothesis that the mean is equal to the mean of the 0–1 ADLs & Score 7+ group. *: Significant at the 95% confidence level **: Significant at the 99% confidence level.
Table 2b: Care needs and care use across cognition score and ADL limitations
| Means | 0 – 1 ADLs & Score7+ | 2+ ADLs & Score7+ | Score 0 – 6 (AllADLs) | Total |
| Cognition score (out of 29) | 13.525 | 10.530** | 4.057** | 11.605 |
| 4.051 | 3.326 | 1.746 | 5.202 | |
| Number of ADLs | 0.056 | 3.682** | 1.433** | 0.512 |
| 0.232 | 1.478 | 2.091 | 1.357 | |
| Number of IADLs | 0.273 | 4.128** | 2.710** | 0.938 |
| 0.816 | 2.540 | 2.862 | 1.965 | |
| Any care (0 or 1) | 0.151 | 0.718** | 0.495** | 0.246 |
| 0.359 | 0.451 | 0.500 | 0.431 | |
| Any Unpaid care (0 or 1) | 0.095 | 0.540** | 0.345** | 0.166 |
| 0.293 | 0.499 | 0.476 | 0.372 | |
| Any Paid care (0 or 1) | 0.076 | 0.353** | 0.259** | 0.125 |
| 0.265 | 0.478 | 0.438 | 0.331 | |
| Any Nursing home (0 or 1) | 0.002 | 0.040** | 0.033** | 0.010 |
| 0.045 | 0.197 | 0.179 | 0.099 | |
| Unpaid care hours per month (conditional on unpaid care) | 42.536 | 84.217** | 69.117** | 60.282 |
| 5.610 | 17.083 | 26.710 | 24.718 | |
| Paid care hours per month (conditional on paid care) | 17.483 | 33.474** | 29.157** | 24.449 |
| 3.371 | 6.846 | 10.158 | 9.777 | |
| NH LOS days per year | 0.055 | 1.609** | 0.652** | 0.252 |
| 1.858 | 22.110 | 8.862 | 6.657 | |
| N | 7,830 | 570 | 1,911 | 10,311 |
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Notes: Standard deviations are in italics. Stars indicate rejection of the null hypothesis that the mean is equal to the mean of the 0–1 ADLs & Score 7+ group. *: Significant at the 95% confidence level **: Significant at the 99% confidence level.
Table 3: Probability of receiving any care
| (1) Any personal care R1 b/se | (2) Any personal care R2 b/se | (3) Any personal care R3 b/se | |
| 2+ ADLs and Score 7+ | 0.547*** | 0.477*** | 0.469*** |
| (0.017) | (0.017) | (0.018) | |
| Score 0 – 6 | 0.332*** | 0.235*** | 0.208*** |
| (0.010) | (0.011) | (0.012) | |
| Age | -0.039*** | -0.042*** | |
| (0.009) | (0.010) | ||
| Age squared | 0.000*** | 0.000*** | |
| (0.000) | (0.000) | ||
| Female | 0.010 | ||
| (0.018) | |||
| Married | -0.079*** | ||
| (0.016) | |||
| Female * Married | 0.046** | ||
| (0.020) | |||
| Number of children | 0.006* | ||
| (0.003) | |||
| Any children | 0.003 | ||
| (0.012) | |||
| Income (Inverse Hyperbolic Sine) | 0.000* | ||
| (0.000) | |||
| Wealth (Inverse Hyperbolic Sine) | -0.000 | ||
| (0.000) | |||
| Primary education | -0.038*** | ||
| (0.009) | |||
| High school | -0.007 | ||
| (0.019) | |||
| College or more | -0.014 | ||
| (0.018) | |||
| Constant | 0.150*** | 1.217*** | 1.407*** |
| (0.004) | (0.364) | (0.385) | |
| N | 10,311 | 10,311 | 9,234 |
| F | 952.101 | 622.665 | 164.851 |
| p | 0 | 0 | 0 |
| R2 | 0.156 | 0.195 | 0.200 |
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Notes: Standard errors in parentheses. * p<0.10, ** p<0.05, *** p<0.01. Omitted category: less than primary education. Proxy respondents identified as cognitively impaired are included in the "Score 0–6" group.
Tables 4a and 4b: Use of formal care on the extensive and intensive margins
| Extensive Margin: Any paid care | Intensive Margin: Hours paid care conditional on receiving any paid care | |||||
| R1b/se | R2b/se | R3b/se | R4b/se | R5b/se | R6b/se | |
| 2+ ADLs and Score 7+ | 0.277***(0.014) | 0.216***(0.014) | 0.213***(0.014) | 15.991***(0.589) | 14.585***(0.528) | 14.732***(0.565) |
| Score 0 – 6 | 0.183***(0.008) | 0.099***(0.009) | 0.096***(0.009) | 11.674***(0.439) | 9.246***(0.413) | 9.290***(0.457) |
| Age | -0.052***(0.008) | -0.047***(0.008) | -1.150***(0.423) | -1.072**(0.454) | ||
| Age squared | 0.000***(0.000) | 0.000***(0.000) | 0.010***(0.003) | 0.010***(0.003) | ||
| Female | 0.025*(0.014) | 0.498(0.731) | ||||
| Married | -0.050***(0.013) | 1.146(0.763) | ||||
| Female * Married | 0.027*(0.016) | -0.523(0.897) | ||||
| Number of children | -0.002(0.003) | 0.230*(0.140) | ||||
| Any children | -0.004(0.010) | -0.933(0.573) | ||||
| Income (Inverse Hyperbolic Sine) | 0.000**(0.000) | 0.000(0.000) | ||||
| Wealth (Inverse Hyperbolic Sine) | 0.000**(0.000) | -0.000(0.000) | ||||
| Primary education | -0.003(0.007) | 0.317(0.416) | ||||
| High school | 0.045***(0.015) | -0.421(0.954) | ||||
| College or more | 0.049***(0.014) | 0.309(0.834) | ||||
| Constant | 0.076***(0.004) | 1.697***(0.294) | 1.516***(0.311) | 17.483***(0.296) | 45.539***(17.055) | 41.387**(18.291) |
| N | 10,311 | 10,311 | 9,234 | 1,291 | 1,291 | 1,147 |
| F | 407 | 360 | 101 | 540 | 431 | 110 |
| p | 0 | 0 | 0 | 0 | 0 | 0 |
| R2 | 0.073 | 0.122 | 0.133 | 0.456 | 0.573 | 0.576 |
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Notes: Standard errors in parentheses. * p<0.10, ** p<0.05, *** p<0.01. Omitted category: less than primary education. Proxy respondents identified as cognitively impaired are included in the "Score 0–6" group.
Tables 5a and 5b: Use of informal care on the extensive and intensive margins
| Extensive Margin: Any unpaid care | Intensive Margin: Hours unpaid care conditional on receiving any unpaid care | |||||
| R1b/se | R2b/se | R3b/se | R4b/se | R5b/se | R6b/se | |
| 2+ ADLs and Score 7+ | 0.45***(0.02) | 0.41***(0.02) | 0.41***(0.02) | 39.87***(2.44) | 39.16***(2.42) | 39.29***(2.59) |
| Score 0 – 6 | 0.25***(0.01) | 0.20***(0.01) | 0.17***(0.01) | 30.86***(2.02) | 30.08***(2.06) | 29.69***(2.31) |
| Age | -0.01(0.01) | -0.02*(0.01) | -8.76***(2.26) | -8.21***(2.45) | ||
| Age squared | 0.00*(0.00) | 0.00**(0.00) | 0.06***(0.01) | 0.05***(0.02) | ||
| Female | -0.01(0.02) | 2.91(3.73) | ||||
| Married | -0.04***(0.01) | 6.95*(3.96) | ||||
| Female * Married | 0.03*(0.02) | -3.05(4.51) | ||||
| Number of children | 0.01***(0.00) | 1.51**(0.63) | ||||
| Any children | 0.01(0.01) | -8.62***(2.73) | ||||
| Income (Inverse Hyperbolic Sine) | 0.00(0.00) | 0.00(0.00) | ||||
| Wealth (Inverse Hyperbolic Sine) | -0.00**(0.00) | -0.00(0.00) | ||||
| Primary education | -0.04***(0.01) | 2.57(1.98) | ||||
| High school | -0.04**(0.02) | 3.19(4.96) | ||||
| College or more | -0.06***(0.02) | 1.59(4.98) | ||||
| Constant | 0.10***(0.00) | 0.21(0.33) | 0.59*(0.35) | 43.85***(1.54) | 385.58***(91.35) | 354.26***(98.82) |
| N | 10,311 | 10,311 | 9,234 | 513 | 513 | 448 |
| F | 747 | 414 | 110 | 169 | 93 | 26 |
| p | 0 | 0 | 0 | 0 | 0 | 0 |
| R2 | 0.13 | 0.14 | 0.14 | 0.40 | 0.42 | 0.46 |
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Notes: Standard errors in parentheses. * p<0.10, ** p<0.05, *** p<0.01. Omitted category: less than primary education. Proxy respondents identified as cognitively impaired are included in the "Score 0–6" group.
Table 6: Use of nursing home on the extensive margin
| (1)Reside in Nursing Home>= 100 daysR1b/se | (2)Reside in Nursing Home>= 100 daysR2b/se | (3)Reside in Nursing Home>= 100 daysR3b/se | |
| 2+ ADLs and Score 7+ | 0.020***(0.003) | 0.017***(0.003) | 0.015***(0.003) |
| Score 0 – 6 | 0.011***(0.002) | 0.007***(0.002) | 0.006***(0.002) |
| Age | -0.001(0.002) | -0.001(0.002) | |
| Age squared | 0.000(0.000) | 0.000(0.000) | |
| Female | 0.005(0.003) | ||
| Married | 0.001(0.003) | ||
| Female * Married | -0.003(0.003) | ||
| Number of children | 0.001*(0.001) | ||
| Any children | -0.005**(0.002) | ||
| Income (Inverse Hyperbolic Sine) | -0.000(0.000) | ||
| Wealth (Inverse Hyperbolic Sine) | 0.000(0.000) | ||
| Primary education | 0.000(0.002) | ||
| High school | -0.002(0.003) | ||
| College or more | -0.003(0.003) | ||
| Constant | 0.001*(0.001) | 0.036(0.063) | 0.028(0.067) |
| N | 10,311 | 10,311 | 9,234 |
| F | 39 | 24 | 6 |
| p | 0 | 0 | 0 |
| R2 | 0.007 | 0.009 | 0.010 |
Source: SHARE (waves 1, 2, 4, 5, 6 and 7). Notes: Standard errors in parentheses. * p<0.10, ** p<0.05, *** p<0.01. Omitted category: less than primary education. Proxy respondents identified as cognitively impaired are included in the "Score 0–6" group.
Table 7: Total cost of long-term care by cognitive score and ADL limitations
| 0-1 ADLs & Score 7+ | 2+ ADLs & Score 7+ | Score 0-6 (All ADLs) | Total | ||
| Formal Care | N | 793 | 63 | 221 | 1,077 |
| Population (millions) | 3.08 | 0.17 | 1.05 | 4.30 | |
| National total (Million €) | 874.50 | 269.18 | 1,096.31 | 2,240.00 | |
| Per user (€) | 751.32 | 1,808.12 | 4,516.58 | 1,717.35 | |
| Per capita (€) | 18.55 | 5.71 | 23.26 | 47.53 | |
| % of GDP | 0.07% | 0.02% | 0.09% | 0.18% | |
| Informal Care | National total (Million €) | 4,743.03 | 1,409.21 | 5,490.76 | 11,643.00 |
| Per user (€) | 2,677.73 | 6,444.20 | 16,097.21 | 5,906.22 | |
| Per capita (€) | 100.64 | 29.90 | 116.50 | 247.04 | |
| % of GDP | 0.38% | 0.11% | 0.44% | 0.93% | |
| Nursing Home | National total (Million €) | 1,750.20 | 2,132.40 | 3,438.40 | 7,321.00 |
| Per user (€) | 4,940.95 | 11,890.84 | 29,702.62 | 13,754.51 | |
| Per capita (€) | 37.14 | 45.24 | 72.96 | 155.34 | |
| % of GDP | 0.14% | 0.17% | 0.27% | 0.58% | |
| Total Cost | National total (Million €) | 7,367.73 | 3,810.80 | 10,025.47 | 21,204.00 |
| Per user (€) | 2,485.10 | 9,962.87 | 16,892.74 | 6,386.75 | |
| Per capita (€) | 156.33 | 80.86 | 212.72 | 449.90 | |
| % of GDP | 0.59% | 0.30% | 0.80% | 1.69% | |
Source: SHARE wave 7. Notes: 2019 euros. See Costa-Font et al. (2025) for clarifications of the calculations. Group national totals are rescaled to add up to the Total column. Per capita figures divide by the total Spanish population.
Este texto se ha extraído automáticamente del documento original. Para citarlo o leerlo con su maquetación, descargue el PDF.
Descargar en PDF